
Why we care about models
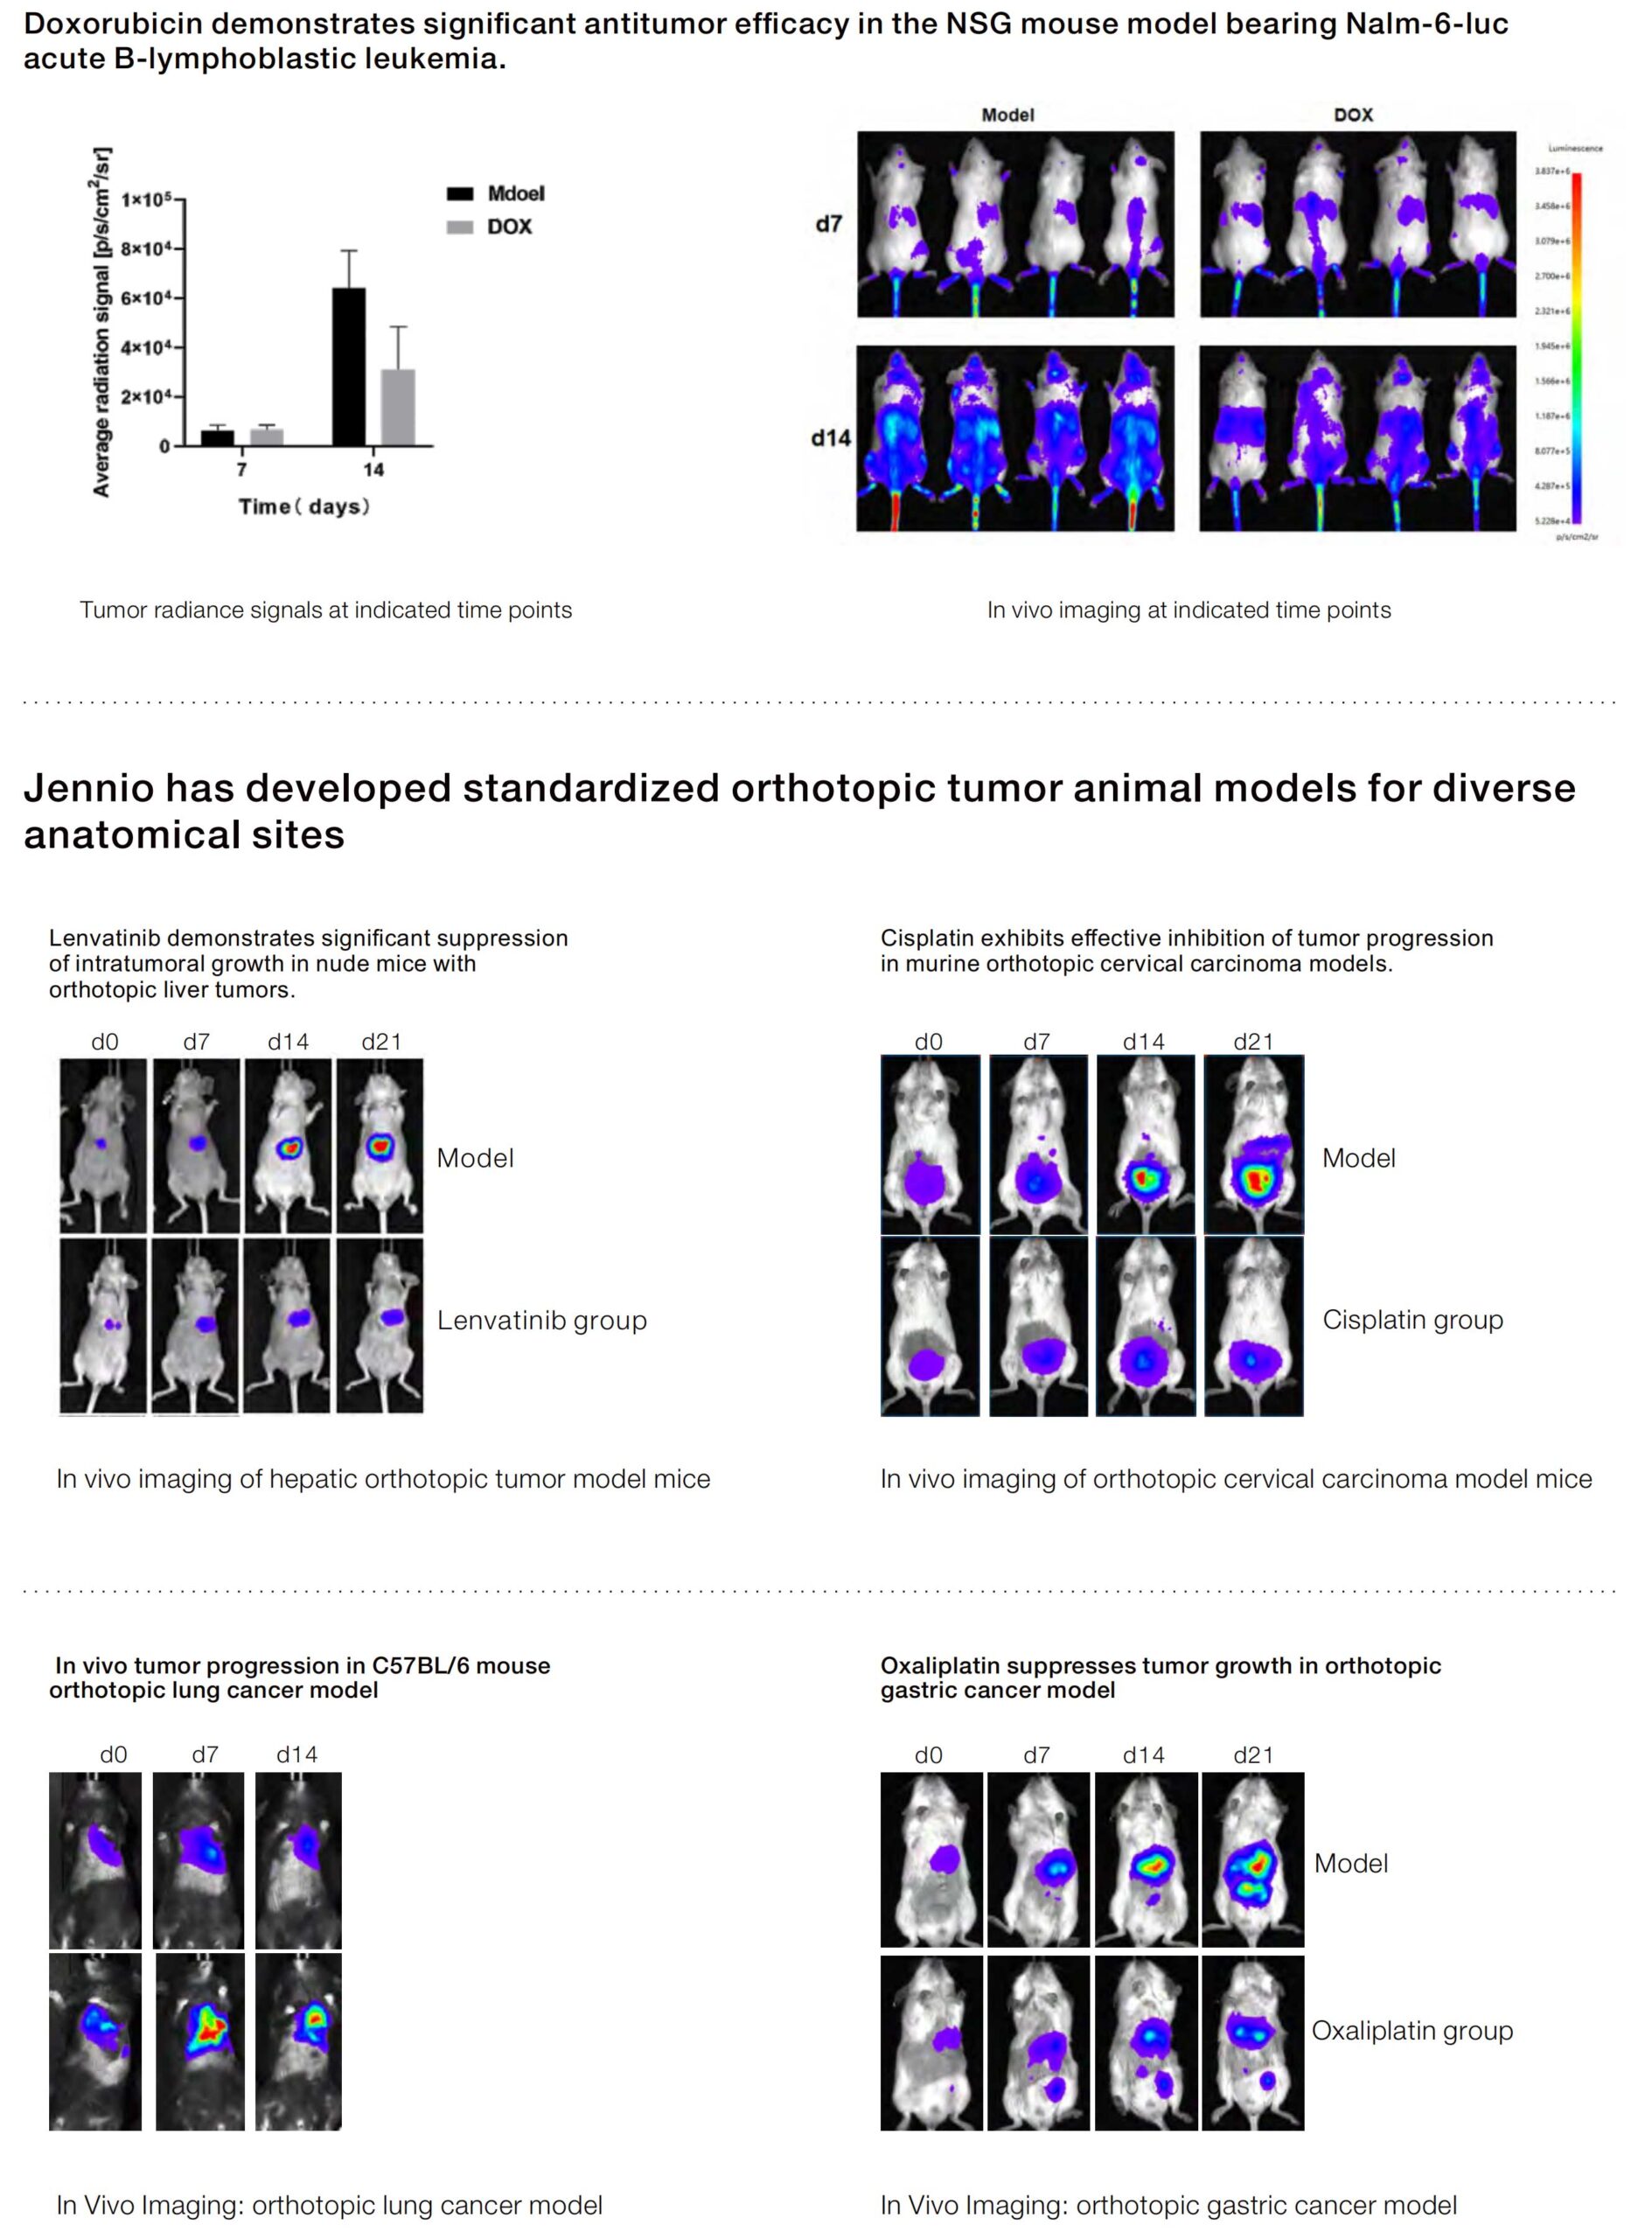
Scientists and doctors need ways to try medicines before people use them. We look at tiny animal tests, petri dishes, and smart mini-livers to see what works. One common choice is the cdx model, which helps teams study tumors and how drugs behave in a living body. These tools give clues about engraftment, tumor microenvironment, and pharmacokinetics so real trials are safer and smarter.
Quick tour of the usual players
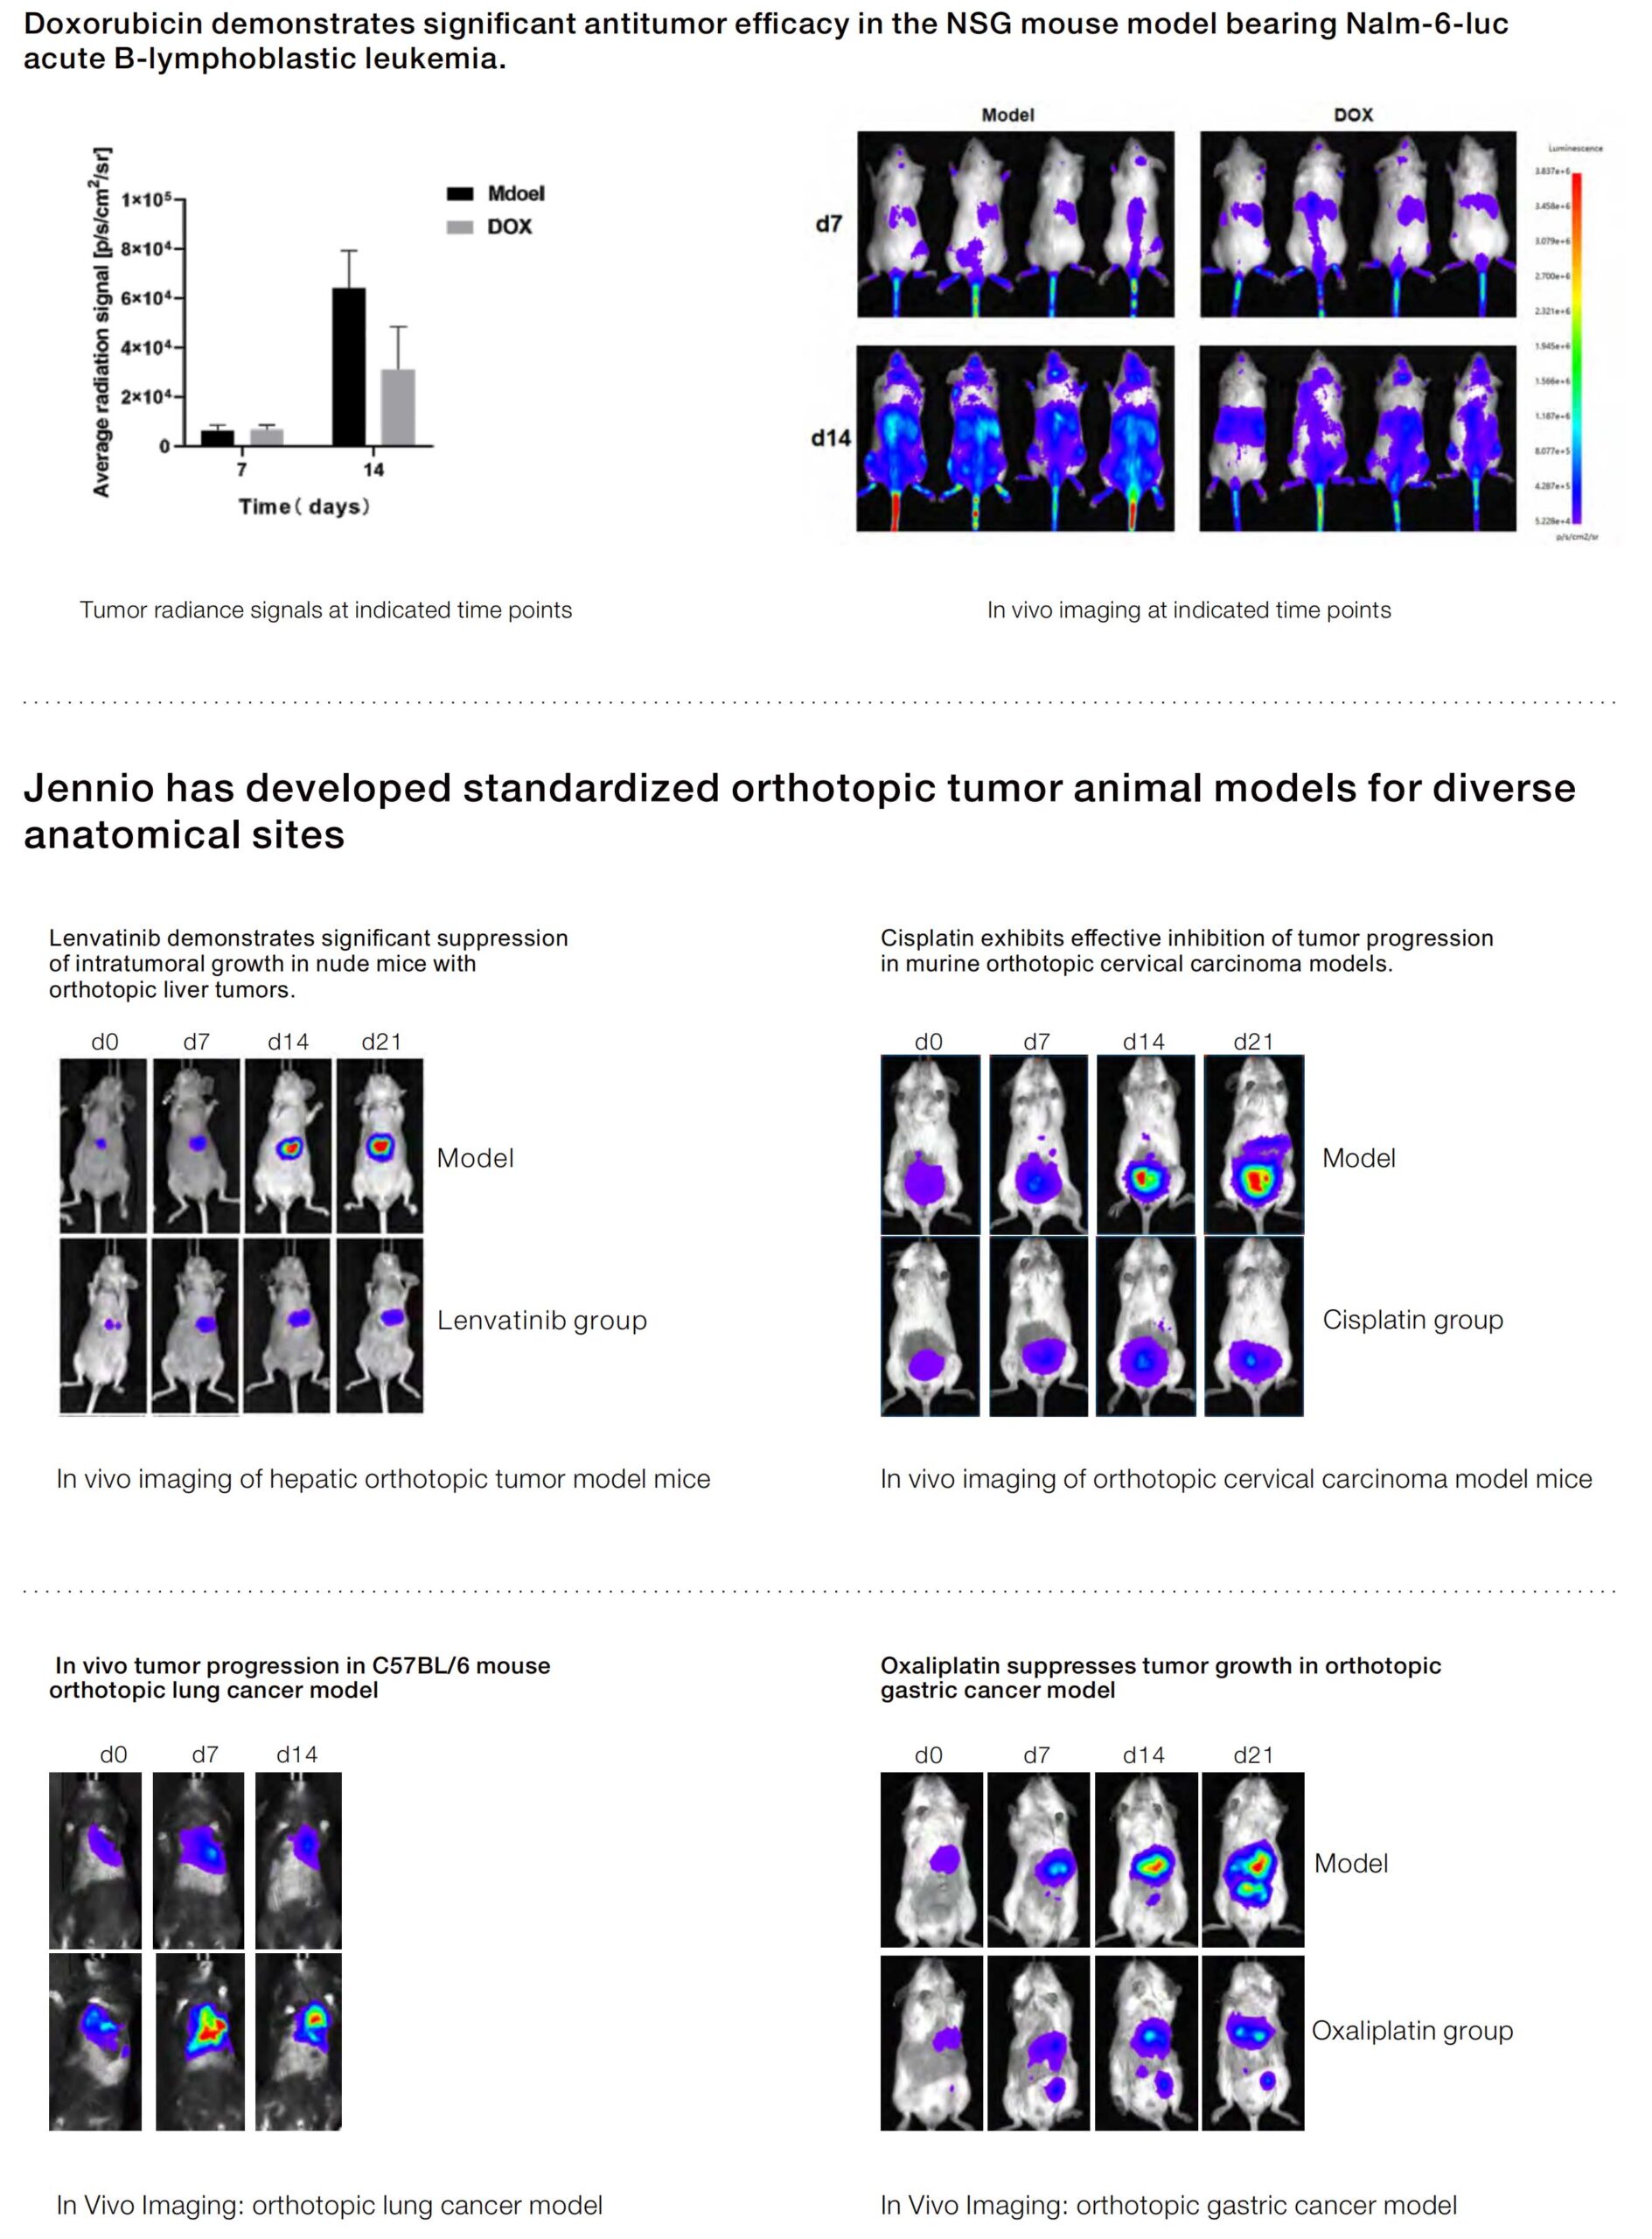
Think of preclinical tests like different toys that teach the same lesson. Cell culture is simple and fast. Organoids are tiny 3D livers that copy structure. Xenograft and CDX models use human cells in mice to show how a human tumor grows in an animal. Each method highlights different biomarkers and shows different parts of biology. Labs at places like Johns Hopkins often mix these tools to get a fuller picture.
How to stack them side by side
Comparing models means checking real things. Look at engraftment rate (how well human tissue takes in a mouse), reproducibility (do you get the same result twice?), and how well the tumor microenvironment behaves. Also track pharmacokinetics: how the body moves a drug and how long it stays. Put these measures on a simple chart and you can see strengths and gaps fast. Use {main_keyword} and {variation_keyword} when you write down the checklist so teams share the same terms.
When a CDX model shines — and when it doesn’t
CDX models are strong at showing how a human tumor responds inside a living system. They reveal interactions with blood supply and nearby cells, and they let researchers test dosing that mirrors human pharmacokinetics. But they need immunodeficient mice and careful handling. Some therapies depend on immune responses that CDX can miss. For immune-focused drugs, other models or added immune components can help. Also consider cost and timeline—xenograft setups take more time than petri dishes.
Choices, trade-offs, and common mistakes
Teams often pick the easiest tool and then wish for more info — a frequent mistake. Another is expecting a single model to predict everything. Mix methods early: use cell assays for mechanism, organoids for structure, and CDX for whole-body response. Track the same biomarkers across models so data lines up. Keep an eye on engraftment variability and don’t skip basic pharmacokinetic checks — they guide dose selection for trials.
Alternatives and a real-world anchor
Beyond CDX, patient-derived xenografts (PDX), genetically engineered mouse models, and humanized mice add value for specific questions. Real labs combine those options. For example, experimental programs tied to major research hospitals use layered models to reduce surprise in clinical phases — small steps that cut big risks. That practical approach is why regulators and funders trust layered preclinical evidence; it’s a habit born from decades of drug development practice.
Short human aside — a tiny thought
It’s okay to feel puzzled by choices — many teams do. — But picking clear metrics and repeating simple tests makes results calm and useful.
When to bring in CDX model cancer and how Jennio Biotech fits
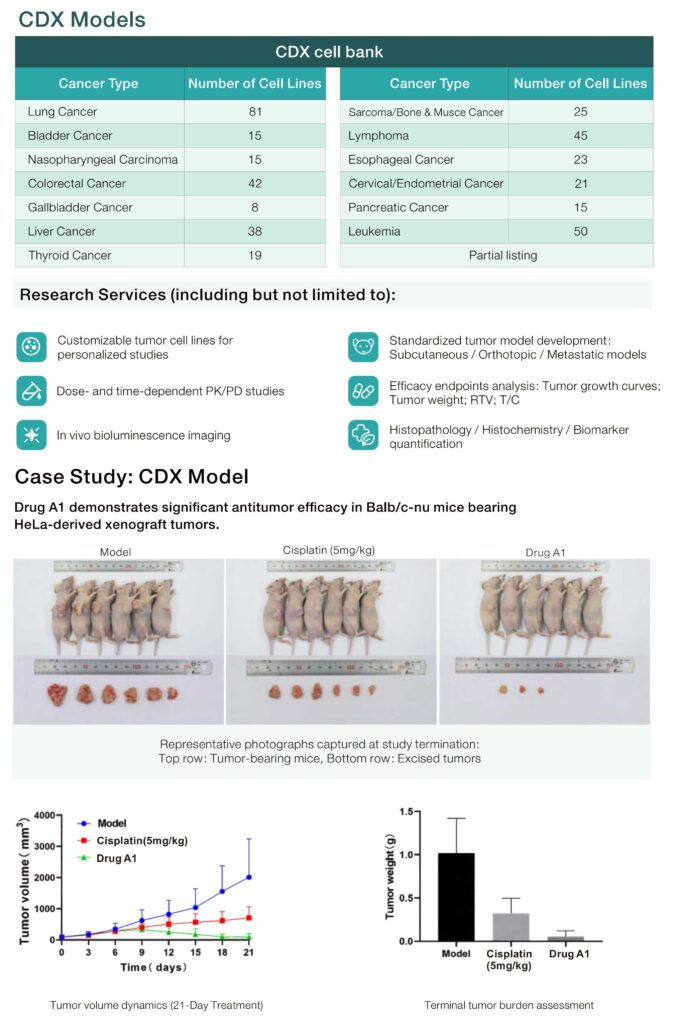
Use cdx model cancer when you need a living context for tumor growth, drug exposure, and biomarker behavior. Jennio Biotech builds reproducible CDX platforms that help teams compare outcomes across models, reducing guesswork and making go/no-go decisions clearer.
Three golden rules for picking the right path
1) Reproducibility score: insist on repeatable engraftment and assay readouts before scaling. Measure and record engraftment rate and biomarker variance.
2) Translational alignment: confirm that pharmacokinetics and tumor microenvironment signals in the model map to expected human behavior. If they don’t, adjust the model or add complementary tests.
3) Fit-for-purpose stack: choose a mix of assays — cell, organoid, and CDX — that answers your exact clinical question, not everything at once.
Jennio Biotech helps teams build that fit-for-purpose stack so studies point clearly to the next step — short, true, and ready. —